Our own product · MedLoop
The clinician sets the plan. We make it happen at home, every day.
MedLoop is an AI-enabled, clinician-led care management platform for the period between visits. One unified care plan covers seven dimensions, so a small clinical team can serve many more patients without drowning in raw data.
A six-step loop: routine work to AI, clinical judgement always with the care team
Why these answers can be shown to a patient
Restricted sources
Answers may only come from the patient's own records, the clinician-maintained specialist knowledge base, and a clinician-reviewed Q&A library.
Citations are mandatory
Every answer a patient sees states what it is based on. Without reliable support, the system does not guess.
Clinician review throughout
Clinicians can read the full conversation and revise any answer they are unhappy with; a revision is never auto-sent to the patient.
Reuse only after approval
Approved revisions enter the knowledge base for future answers — each correction becomes a standard answer.
Explicit boundaries
AI does health education and plan execution. It does not diagnose, and no plan reaches a patient without clinician confirmation.
Patients
A WeChat mini-programme (no download) and the MedLoop app: daily tasks, symptom reporting, record management, questionnaires and the AI assistant. App notifications and AI voice calls reach patients between visits.
Clinicians
Mini-programme, app and web console: plan management, risk alerts, record review, proactive outreach, AI answer review, panel management and knowledge-base maintenance.
The actual product
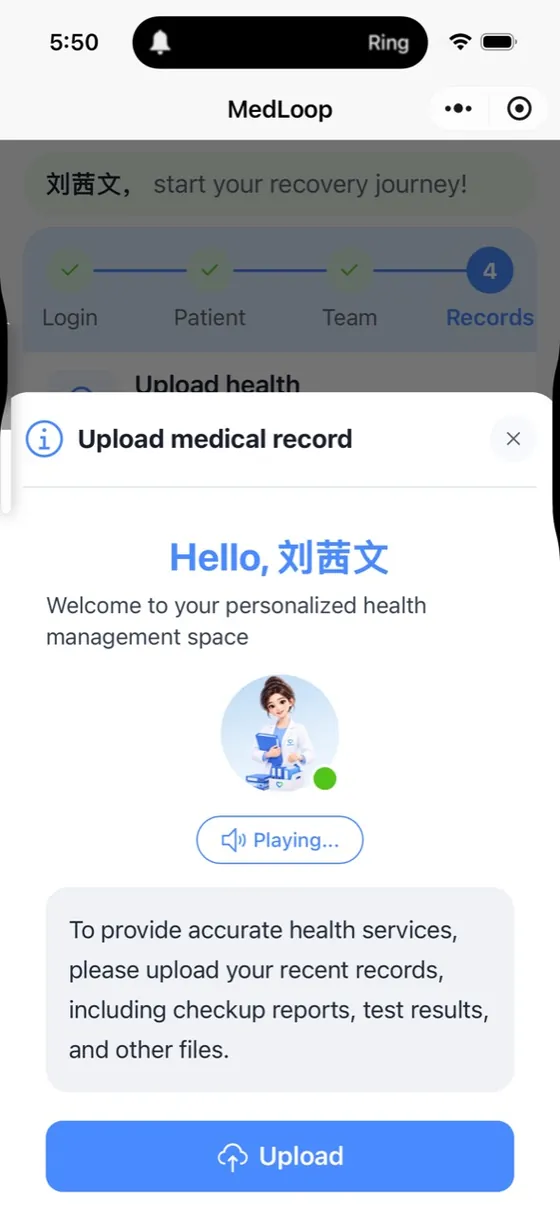
Voice-guided onboarding gives older adults a clear next step
Automatic audio guidance makes first use easier for older adults.
Patients are invited to upload records, set health goals and complete assessments.
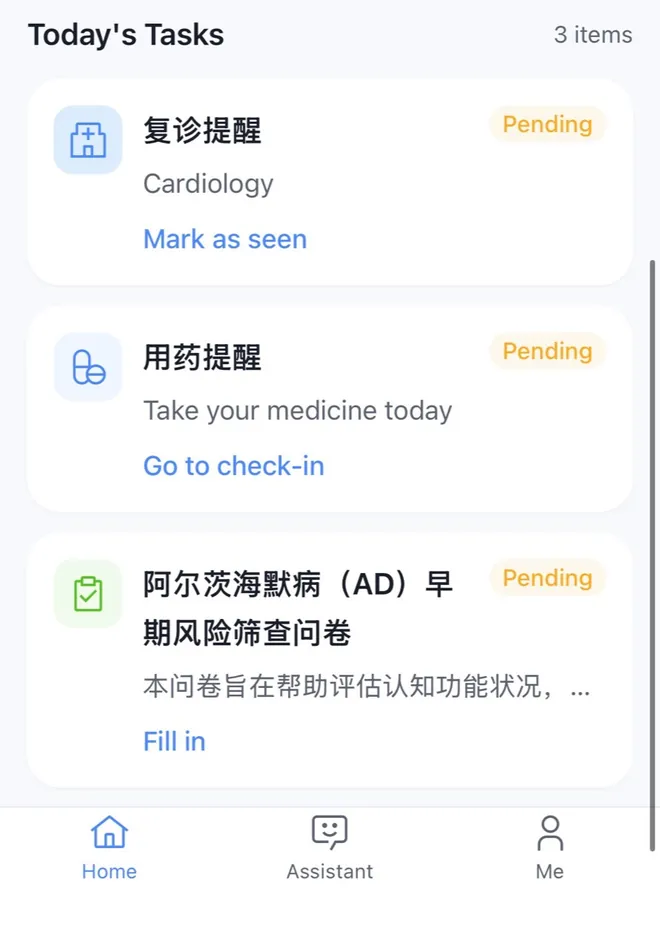
Today's Tasks turns instructions into action
Care instructions from plans, questionnaires, medication guidance and records appear at the right time.
The patient always has a clear answer to: \u201cWhat should I do today?\u201d
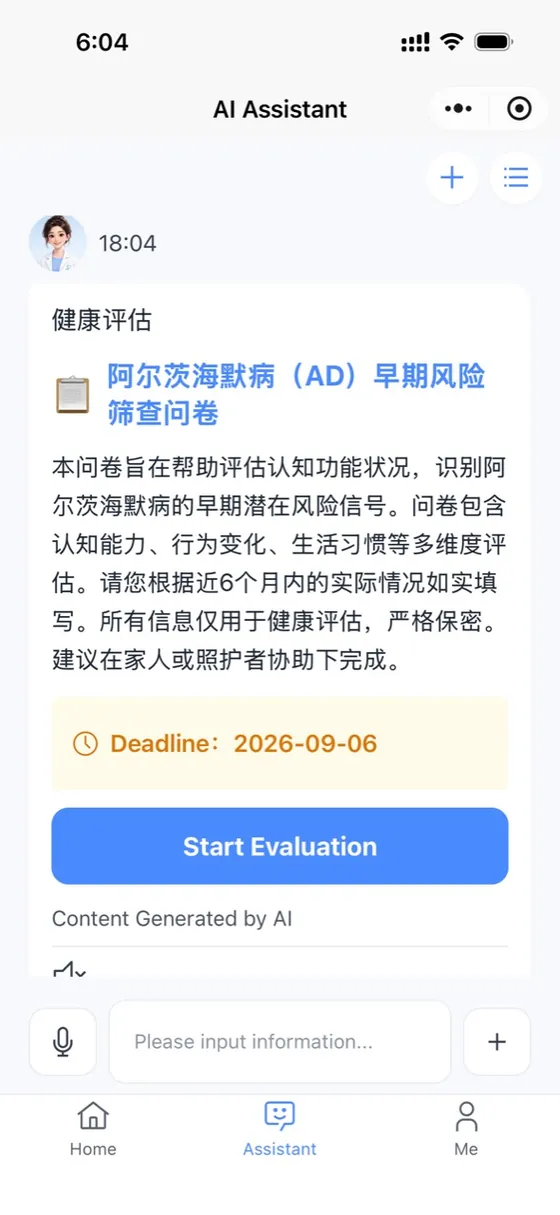
A questionnaire agent turns an uploaded form into a guided conversation
The clinician uploads an existing questionnaire. The agent orchestrates an interactive assessment around its content.
When the conversation drifts, the agent returns to the flow and summarises the dialogue as structured data for the clinician.
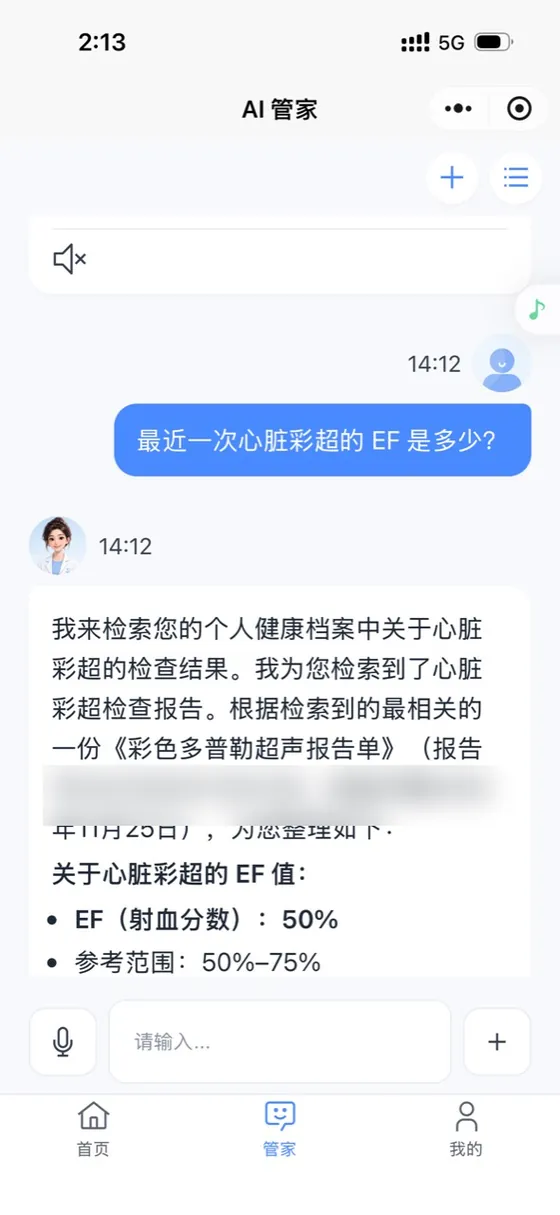
Every patient-facing answer requires a traceable source
The assistant searches three governed sources: the patient record, the clinician-prepared specialty knowledge base and the reviewed Q&A library.
Source citation is mandatory. If the approved sources cannot support an answer, the assistant says so instead of guessing.
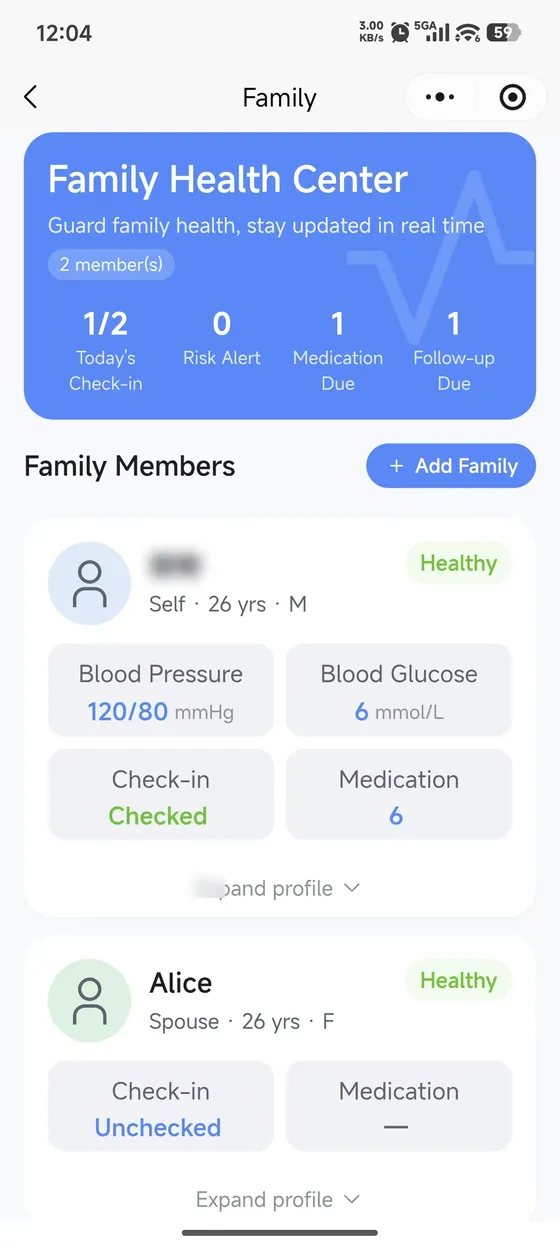
Patients and families share daily care responsibility
Care teams cannot observe every moment at home. Patients can bind directly with family members and share relevant care information.
If a patient misses medication or another task, MedLoop notifies the patient and can alert the family.
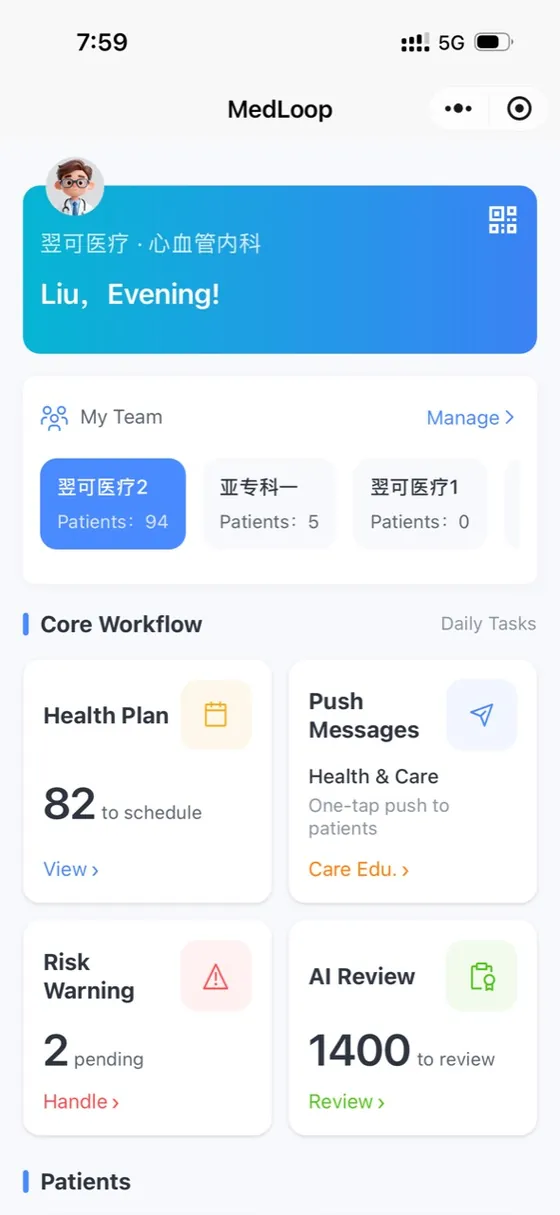
The clinician home screen organises the day's essential work
Health plans, outreach, risk warnings and AI review appear as focused work queues.
Mobile access supports timely action between consultations.
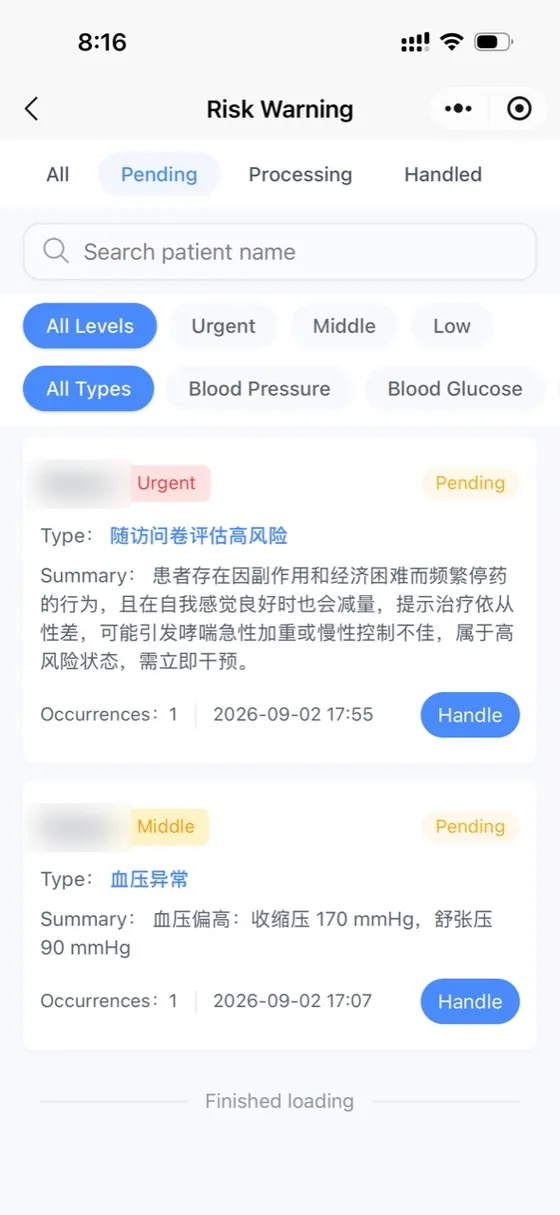
Scattered warning signals become a prioritised clinical queue
Warnings are structured by severity, type, summary, occurrence, time and handling status.
The tool supports exception management. It does not make an autonomous diagnosis.
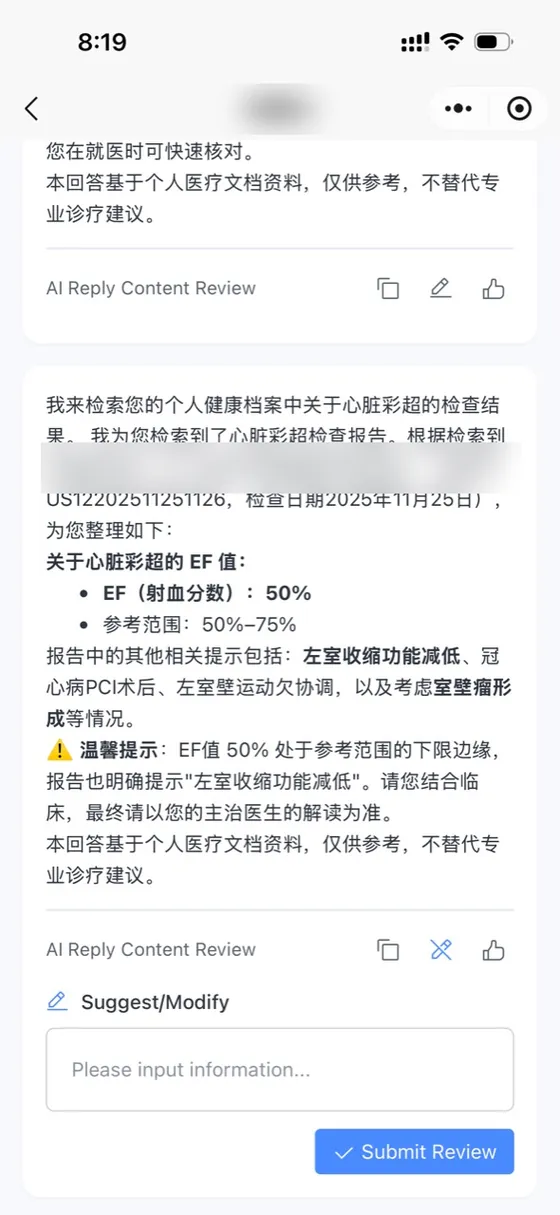
Clinician corrections strengthen governed knowledge
Unsatisfactory AI content can be reviewed, edited and submitted for controlled reuse.
Edits do not automatically become direct messages to patients.
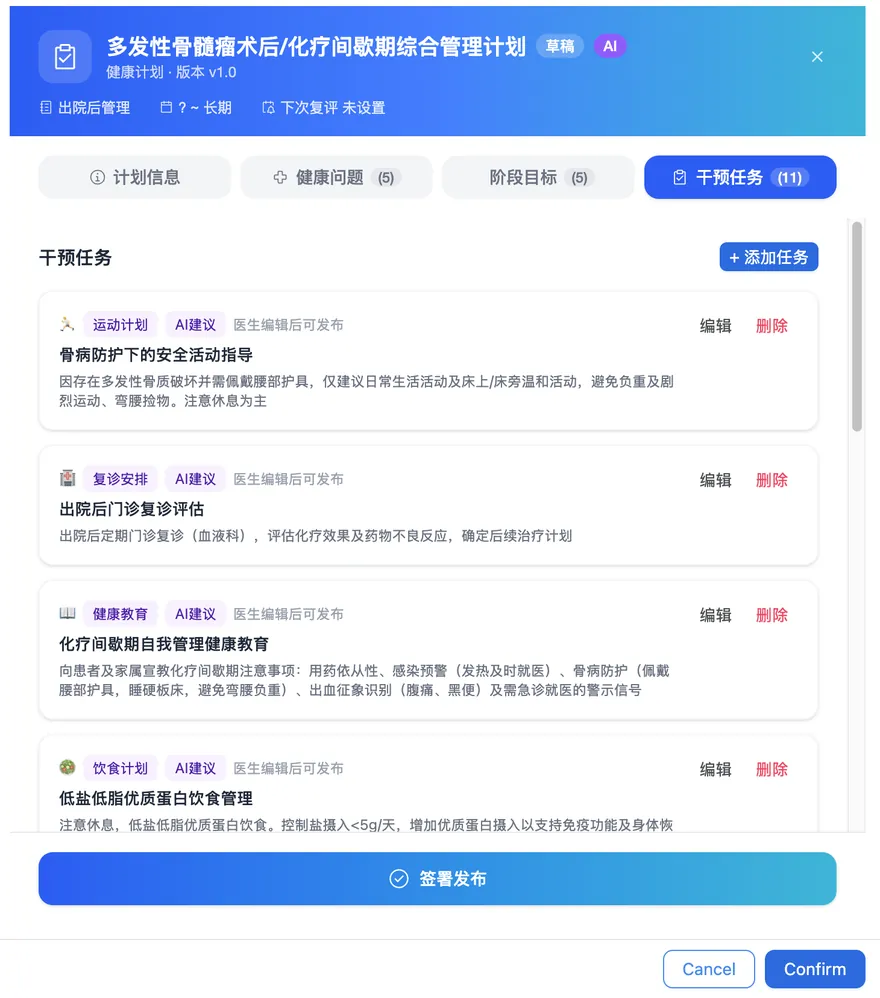
Goals become personalised interventions patients can execute
Suggested tasks cover activity, revisit arrangements, education, diet and other daily actions.
Every AI suggestion is editable and requires clinician publication.
Real product screens. Patient names and report identifiers are redacted. Several screens show the Chinese production interface.
Interactive R&D prototypes
Risk-alert loop
A clickable demo across clinician app, patient app and mini-programme — rule configuration, alert triage, re-measurement, closure and record write-back — with per-screen product, front-end/back-end and API spec panels.
Open prototype →Clinical trial design module
End-to-end workflow and three-end touchpoints: web-console protocol design, freeze, batch screening and data QC; the clinician app, the patient app, and billing and activation.
Open prototype →Where it actually stands
Current status by site; client names are anonymised.
- Haematology, a tertiary hospital in ChinaIn productionMultiple myeloma follow-up, daily care management and prospective cohort collection; 100+ real patients enrolled
- Cardiology, same hospitalTraining and rolloutPatient and family onboarded after the surgical consultation; post-operative follow-up and ongoing Q&A
- Geriatrics, same hospitalTraining and rolloutTeam management linking specialists for multidisciplinary care of complex older patients
- Health management centre, a tertiary hospitalTraining and rolloutAfter the check-up report is explained, high-risk individuals enrol for ongoing management and AI Q&A
- A municipal hospital and partner primary-care sitesIn preparationRegional quality control through team collaboration and record review; planned coverage of 1,000 tuberculosis patients
Security: what is implemented, and what we verify before any pilot
Implemented
- HTTPS transport encryption
- AES encryption on sensitive fields
- Role-based authorisation
- Isolation by institution, team and patient
- Audit trail on key operations
Verified before any pilot
- Encryption of source files
- Backup and disaster recovery
- Production / test environment separation
- Patient consent, retention and deletion
- Incident response and local compliance
Our cross-border position: each jurisdiction gets its own servers and data does not leave it. Security commitments are made against the actual deployment and verified controls, never in the abstract.
Who pays depends on the programme
Families · subscription
Ongoing support for the patient, family co-management and plan execution.
Departments and hospitals · services
Pilots, joint clinical pathway design, operations and private deployment.
Pharma and programme partners · sponsorship
Disease management, patient support, screening, research or public health programmes.
Pricing and cost-benefit are to be validated in a pilot. We start where the responsible clinician is clear, the pathway is defined, and the result can be measured.
Next step: one focused pilot
Focus page · Screening and pharma
Who catches the patient in the three years after a positive result
Screening solves detection. Medicine solves treatment. The stretch that actually decides the outcome — what happens at home, every day — has had no owner. That is the stretch MedLoop covers, and it turns it into measurable, recoverable data.
One loop, from screening to real-world evidence
For screening and diagnostics manufacturers
Turn a single test into a period of service
After a positive or high-risk result, what the patient needs most is what to do next. From enrolment they can ask questions against a clinician-governed knowledge base — even before results are back.
Keep high-risk, undiagnosed people engaged
Retest reminders, symptom check-ins and education follow the clinician's chosen rhythm, so fewer high-risk individuals fall out of view.
Build the channel together
Check-up centres, health management centres and specialist clinics all work as enrolment points; the same flow serves every channel without rebuilding.
For pharmaceutical companies and programme partners
The execution layer of a patient support programme
Turn a support programme on paper into tasks the patient completes and a completion rate you can track.
Adherence and treatment persistence
Older patients carry several conditions and several prescriptions; understanding instructions is not the same as following them. Adherence is recorded with its source and quality and compared against what the plan expected.
Structured real-world data
The same flow supports on-time treatment and adverse-event monitoring while accruing prospective data on different interventions.
Sponsorship, programme by programme
Disease management, patient education, screening and public health programmes can all be sponsored per programme, with the responsible clinician and pathway agreed first.
Boundaries we write down before being asked
- AI performs health education and plan execution. It does not diagnose and does not replace clinical judgement; no care plan reaches a patient without clinician confirmation.
- No efficacy claims, and no commercial influence on prescribing decisions; content and the clinician review chain are fully auditable.
- Patient data stays within its jurisdiction. Research use requires patient authorisation and follows local data protection and healthcare advertising rules.
- Commercial work is signed per programme, with payer, data use and responsible clinician agreed in writing before kick-off.
Contact
Start with one conversation about the case
If you have a specific case — one production line, one faculty, one department, one clinical pathway — we'll do a feasibility conversation at no charge and tell you whether it's worth building.